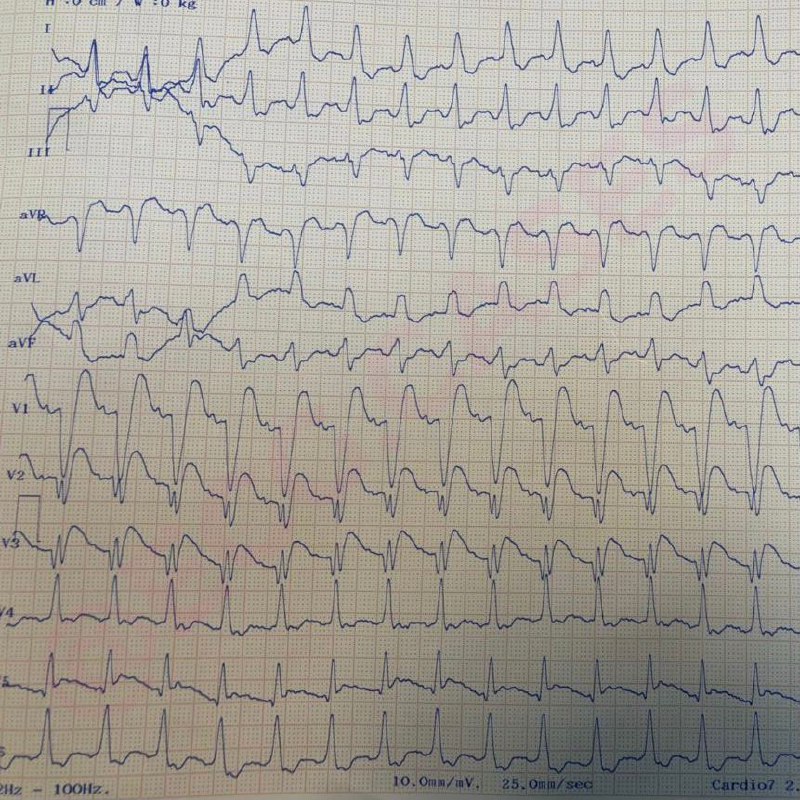
In antidromic AVRT anterograde conduction occurs via the accessory pathway with retrograde conduction via the AV node. Stable patients may respond to drug therapy including amiodarone, procainamide or ibutilide, but may require DC cardioversion. In a haemodynamically unstable patient urgent synchronised DC cardioversion is required. If in doubt treat as VT !
There is a regular, broad complex tachycardia at ~150 bpm; this rhythm is distinguished from VT by the presence of followings:
• Delta waves (best seen in leads D2, aVF, V3 and V4) • Retrograde p waves with an RP interval>70ms (best seen in inferior leads D2, V4 and V5) • electrical alternans • ST elevation in aVR and ST depressions in most leads (not a specific finding)
 EC